Author: Louise Stanley

£50m funding to cure – rather than control – inflammatory diseases

Birmingham researchers are now part of the new £50m UKRI Medical Research Council (MRC) Centre of Research Excellence (CoRE) for Restorative Immunology, seeking to find curative treatments for inflammatory diseases alongside team of leading scientists, doctors and patient research partners.

Diseases caused by chronic inflammation – such as arthritis, inflammatory bowel disease, autoimmune liver disease and Sjögren’s disease – currently require lifelong management. However, this new programme of research is aiming to kickstart a transformation in understanding the causes of inflammatory disease, with the ultimate aim of developing cures.

The MRC CoRE is funded for the next 14 years and is led by a team of investigators from across the UK and Japan, aiming to transform the lives of people facing debilitating immune-mediated diseases.

As well as being a major burden for individuals, chronic inflammation has a considerable impact on health services and the wider economy. These conditions arise when the body’s immune system mistakenly attacks healthy tissues, including joints and the gut, skin, eyes, liver, and salivary glands, among many others. The resulting inflammation can cause irreversible tissue and organ damage, chronic pain and lifelong disability.

Despite major advances in treatment, many people, including those whose disease begins in childhood, require lifelong therapy to control inflammation and prevent further damage. The impact can be profound, affecting health, independence and quality of life.

Professor Adam Croft, from School of Infection, Inflammation and Immunology, the Arthritis UK Chair of Rheumatology and Director of the MRC CoRE in Restorative Immunology said: “While remarkable advances have been made in the treatment of immune-mediated inflammatory diseases over the past two decades, the focus has largely been on controlling inflammation to relieve symptoms and prevent damage to tissues.

“New technologies now allow us to study diseased tissues at unprecedented resolution, revealing how healthy tissue becomes diseased and identifying the cells and molecular pathways that drive this process. Combined with the development of therapies capable of precisely targeting these cells and pathways, this creates a realistic opportunity to move beyond lifelong disease control towards treatments delivered with curative intent – with the ultimate goal of restoring long-term health and wellbeing.”

Alongside Professor Adam Croft, who is an active researcher at both the University of Birmingham and the University of Oxford, Birmingham researchers will join this programme, contributing strengths integral to the success of the MRC CoRE including: human tissue modelling; experimental medicine; and early clinical studies.

The University of Birmingham has also attracted major global partners to join the ambitious programme. Professor Ye Oo is Chair of autoimmune liver diseases and translational hepatology and will lead liver theme of MRC CoRE. Prof Oo’s recent Wellcome Discovery Award with Nobel Laureate, Professor Shimon Sakaguchi from Osaka University will underpin early phase translational trials.

Alongside leading experts for specific conditions covered by the MRC CoRE, the University of Birmingham will look at vital cross-cutting workstreams such as inclusive research design and data equity and generalisability.

The CoRE will build on best practice approaches developed in Birmingham, including Artificial Intelligence-focused project STANDING Together and REP-EQUITY, which helps reduce health inequity in research. The underpinning support will ensure the data underpinning the programme represents patient experiences of health burdens, while pioneering statistical approaches.

Dr Ameeta Retzer, an Associate Professor at the University of Birmingham’s Centre for Evidence and Implementation Science said: “The MRC CoRE for Restorative Immunology represents a transformative opportunity for people with immune mediated inflammatory diseases (IMID). The inclusion of key programmes such as REP-EQUITY will ensure it doesn’t leave anyone behind.”

The team will bring together experts from eight universities, charities, public engagement organisations, industry and biotechnology, combining different skills and perspectives to improve the lives of patients and train the next generation of researchers.

Dr Ceri Williams, Executive Director of Challenge Led Portfolio at MRC, said: “MRC Centres of Research Excellence are designed to tackle some of the most important challenges in biomedical research through sustained, ambitious and collaborative science. By doing so, they contribute to UKRI’s mission to advance knowledge, improve lives and drive growth across the UK.

“By bringing together expertise from across disciplines, sectors and countries to tackle these fundamental questions, this centre has the potential to transform our understanding of inflammatory disease and accelerate the development of treatments that deliver lasting benefits for patients.”

Birmingham expert chairs Independent Commission on safe AI adoption in healthcare

A Birmingham clinical academic has co-chaired a new report setting out how the NHS can adopt AI innovations while maintaining public trust and patient safety.

Professor Alastair Denniston of BHP founder-member the University of Birmingham has chaired the National Commission into the Regulation of AI in Healthcare which has published its recommendations on how the UK can strengthen the regulation of AI in healthcare – ensuring it remains safe, keeps pace with innovation, and continues to earn people’s trust.

AI is already used in the NHS to spot serious health problems early, for example strokes and skin cancers, and to free up clinicians’ time through voice-enabled technologies. The Commission’s recommendations aim to help more patients benefit safely and quickly, by supporting the UK to become the best place for innovators to build and safely test AI, the best place for healthcare professionals to use it and – most importantly – the best place for patients to engage with it in their care.

Professor Denniston, who Chairs the National Commission into the Regulation of AI in Healthcare, said: “We innovate because we believe tomorrow’s healthcare can be better than today’s. But any new innovation – including AI – needs to earn its place and earn our trust. These technologies need to show that they are safe, effective and bring benefits to patients, staff and the wider NHS, without leaving people behind.

“Over the past year we have heard from more than 12,000 people, including patients, carers, clinicians and the technologists building AI tools. One message came through clearly: people are open to AI improving their care, but only if it is safe, overseen by humans, and if they know when it is being used. These recommendations are designed to make that trust possible, so that the UK can lead the world not just in developing AI for healthcare, but in showing how it can be regulated and used responsibly.”

Among the key recommendations in the report, the Commission proposes a pathway for faster access to safe and effective AI.

The Commission recommends that the MHRA introduce staged authorisations for new AI models, similar to ‘L-plates’ for learner drivers. New models would be deployed under close supervision and tight guardrails, allowing them to demonstrate real-world safety and performance before being granted fuller authorisation. This staged approach is designed to give UK patients world-first access to promising new models, while ensuring risk is carefully controlled at every step.

Other recommendations include:

  • Continuous, real-world monitoring throughout a device’s lifecycle. Rather than a single, point-in-time approval, the Commission recommends that AI-enabled medical devices should be subject to continuous, real-world monitoring throughout their working life;
  • Public access to safety information. The Commission also recommends that members of the public should be able to easily search for information about the safety of specific AI-enabled medical devices, including any adverse incidents; and
  • Tougher powers to protect patients. The Commission recommends stronger powers for the MHRA, including enhanced enforcement powers, to ensure that where AI systems fall short of the standards patients expect, the regulator can act decisively.

Professor Henrietta Hughes, NHS General Practitioner, Deputy Chair of the National Commission and Patient Safety Commissioner for England, said: “Patients have told us that to trust AI is safe, they want to know when it’s used, that it supports rather than replaces clinicians, and that there is clear accountability if things go wrong. That’s exactly what our recommendations deliver.

“Putting people before technology to improve care and give clinicians more time to meet patients’ needs. That’s how we can keep people safe and build the health system’s confidence to embrace AI’s full potential.”

Lawrence Tallon, the MHRA’s Chief Executive said: “I welcome this authoritative and independent report which sets out in more detail than ever before how we should best regulate AI in healthcare.

“We have heard clearly about the opportunities of AI to speed up and improve care, and to release more of clinicians’ time for the essentially human aspects of their work with patients.

“We will only realise those opportunities if we have a modern, dynamic regulatory framework that accelerates safe adoption, protects patients and commands public and professional confidence. I am so grateful to the many people who contributed to this expert Commission to set out the roadmap ahead.”

The independent Commission was established by the Medicines and Healthcare products Regulatory Agency (MHRA) in September 2025 and includes diverse expertise across health, regulation and AI, including international contributors from around the world including the USA and Singapore.

The Commission gathered evidence from more than 12,000 people over the course of a year, including patients, the public, clinicians, healthcare leaders, industry and technology developers, making it the largest engagement of its kind ever undertaken in the UK on the regulation of healthcare technology. Additional in-depth deliberative research by research partner the Health Foundation with members of the UK public, published today, provided detailed insight into the UK public’s priorities and expectations for the regulation of AI in healthcare.

Taken together, that engagement found broad public support for AI in healthcare, with clear conditions: strong safety standards, meaningful human oversight, and transparency about when and how AI is being used in someone’s care. The Commission’s recommendations respond directly to these views.

Non-invasive test identifies more than 9 in 10 bladder cancers, clinical study finds

More than 9 in 10 patients who had bladder cancer were picked up through a non-invasive urine test after urgent referral, a new study has found.

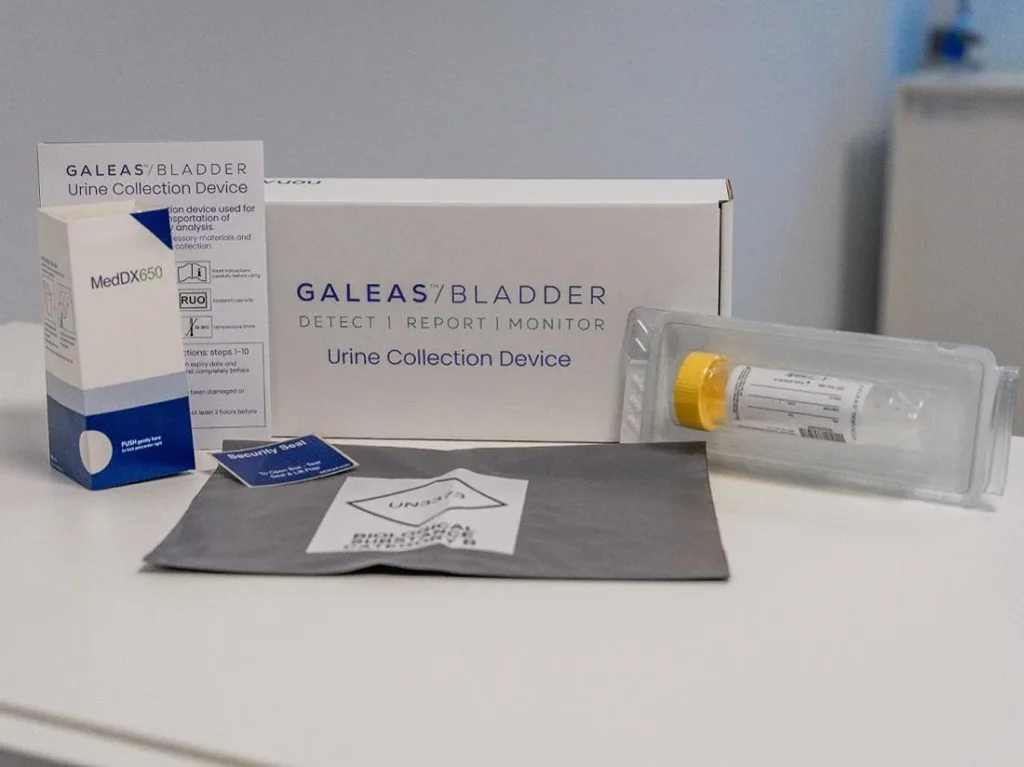
Study of 964 patients across seven NHS urology units found that the test detected 71 of 77 bladder cancers (92.2%) among the nearly 1,000 patients. The study, led by the University of Birmingham and Nonacus Ltd, investigated the real-world significance of testing for bladder cancer using a commercially available urine test –  GALEAS™ Bladder, which tests genomic information from a patient’s urine for traces of bladder cancer.

The peer-reviewed results have been published in European Urology Oncology, and showed significant results for detecting cancer as well as its use as a screening tool.

GALEAS Bladder detected all 17 muscle-invasive bladder cancers (100%) and 35 of 36 high-grade cancers (97.2%) diagnosed during the study. Meanwhile, a negative result was associated with a 99.3% probability of not having bladder cancer.

For the 30% of patients in the study with blood in their urine but which was not visible to the naked eye (non-visible haematuria), GALEAS Bladder identified all bladder cancers (100%) with a negative result associated with a 100% probability of not having bladder cancer.

Professor Richard Bryan, Director of the University of Birmingham’s Bladder Cancer Research Centre and co-author of the study, said: “We have spent many years developing and evaluating the science behind detecting bladder cancer through DNA in urine with support from Cancer Research UK and philanthropists, ultimately leading to the development of the GALEAS Bladder test by Nonacus. This prospective study shows that the very promising early performance has now been reproduced across multiple NHS centres and in a large real-world patient population.

“GALEAS detected 35 of 36 high-grade cancers and every muscle-invasive cancer diagnosed in the study. These results show that molecular urine testing can be used now to help clinicians decide which patients need an urgent cystoscopy and which can safely have that procedure deferred.

“The results are very significant for clinical practice. Only 8% of patients in the study were ultimately diagnosed with bladder cancer, which highlights the challenge facing NHS haematuria services where large numbers of patients currently enter the same urgent diagnostic pathway despite most not having cancer. GALEAS is a promising and less invasive test that can be easier to administer and make testing and screening for bladder cancer far easier.”

The GALEAS test was used in the study alongside a typical way to test for bladder cancer using a technique called cystoscopy. In a cystoscopy test, a camera is passed through the urethra to examine the bladder. The procedure is an important part of bladder cancer diagnosis, but Professor Bryan, a former clinical urologist, notes that the procedure is invasive and resource intensive.

GALEAS Bladder uses DNA found in a urine sample to help clinicians identify patients at greater risk who should be prioritised for urgent cystoscopy, while allowing cystoscopy to be deferred for some patients at lower risk where clinically appropriate.

Lee Silcock, Co-founder and Chief Product Officer at Nonacus and co-author of the study, said: “Seeing GALEAS perform so strongly across almost 1,000 patients in seven NHS urology departments is extremely encouraging. This is real-world evidence from the patients and pathways the test has been designed to support.”

“What matters most is identifying those most likely to have cancer sooner, while giving clinicians confidence when deciding which patients can safely wait for a cystoscopy. The fact that the test detected every muscle-invasive cancer in the study, alongside a negative predictive value of more than 99%, gives us further confidence in the role GALEAS can play in supporting NHS diagnostic pathways.”

The study also found that incorporating urine-based testing in bladder cancer pathways could reduce the burden on urology departments. At the most cautious pre-specified clinical threshold, using GALEAS Bladder to triage patients was estimated to result in 730 fewer urgent cystoscopies for every 1,000 patients, compared with urgent cystoscopy for everyone, with no loss of net clinical benefit.

GALEAS Bladder is already being used within NHS pathways in England and Wales, with further NHS sites adopting the test as clinical use expands.

Aston University’s health researchers to help guide redesign of Birmingham and Solihull’s NHS

Aston University is partnering with fellow BHP members Birmingham Community Healthcare NHS Foundation Trust (BCHC)  to build better joined-up health and care services in local neighbourhoods across Birmingham and Solihull.

This new approach aligns with the government’s 10-year health plan to create a Neighbourhood Health Service by moving care out of large hospitals and closer to people’s doorsteps, shifting focus towards preventing illness and moving from analogue systems to more efficient digital technology.

The three-year Knowledge Transfer Partnership (KTP) project will develop England’s first comprehensive system for monitoring how these changes impact patients and staff. It will provide critical metrics on people’s health, their experiences of care, and the well-being of NHS staff, so that continuous improvement can be guided by a detailed understanding of what works well.

To guide this transformational piece of work, health and organisational management researchers across Aston University will work with BCHC to develop a monitoring system to measure outcomes as each service and clinic is redesigned. This will combine qualitative methods, systems mapping and big data.

The system will measure patient experiences of care and help determine whether clinical outcomes are being achieved as services improve – such as reducing the likelihood of falls, preventing acute and critical illness, or better managing chronic conditions. It will also map the efficiency and flow of patients between hospital, community and home so that staff can rapidly intervene in the event of bottlenecks or delays.

For staff, the system will measure wellbeing, caseload and travel burdens as they move into community hubs across the city. These insights will enable the Birmingham and Solihull health and care services to operate an integrated community care system that is more sustainable for staff and can be continuously improved.

As other UK towns and cities look to redesign their health and care services in response to the UK government’s 10-year plan for the NHS, the Birmingham and Solihull model could offer a blueprint for others to learn from.

The KTP project will be led by researchers in Aston University’s Institute for Health and Neurodevelopment, Aston Business School and Aston Pharmacy School. They will bring expertise in developing and deploying data-driven methods for evaluating health services and community care projects, tried and tested through existing partnerships with the NHS.

Professor Rachel Shaw, associate director for researcher development (academic) at the Institute of Health and Neurodevelopment at Aston University, leads the KTP. She said: “Every NHS system is unique to the community it serves. We’re building an evidence-based way to monitor and guide the redesign of a health system that will be fit for the future and reusable for other organisations. Effective evaluation will support staff tasked with running NHS services across Birmingham and Solihull and empower them to continuously improve those services based on evidence. We want to see how staff as well as patients can benefit from care in the community, so that this programme can be a guiding light for other NHS systems across England.”

Dr Robbie Dedi, chief medical officer for BCHC, said: “Making it easier for citizens to access the care and support they need, when and where they need it, is the driving force behind the city’s transformation of health and care services. Our partnership with Aston University will be critical for enabling us to better identify and tackle health inequalities, so we can make services fairer and more accessible for everyone. The new monitoring systems we’re setting up together will guide us in what works, what needs to be improved and whether we’re managing our resources effectively. This will be the first major evaluation of how integrated care functions across Birmingham and Solihull.”

Knowledge Transfer Partnerships, funded by Innovate UK, are collaborative projects that bring together a business, an academic partner, and a qualified associate to deliver strategic innovation and business improvement. Aston University is a national leader in the programme, ranked joint-first in the UK for volume of active projects and first for overall project quality.

For further details about this KTP, visit www.aston.ac.uk/business/collaborate-with-us/knowledge-transfer-partnership/at-work/health-care-system.

Clinical fellowship opportunity – West Midlands Secure Data Environment

Birmingham Health Partners, in partnership with the West Midlands Secure Data Environment (WMSDE) and the Dexter platform team, is pleased to invite expressions of interest from clinicians in maternity and acute care to join our collaborative research and data innovation program.

About WMSDE and Dexter

WMSDE is an NHS platform that enables secure access to linked health and care data to approved users for research. WMSDE works in partnership with health and care organisations within the region to bring together disparate health information into linked multi-modal datasets for technology evaluation, clinical trials, translational studies, and real-world assessment of treatments and healthcare delivery systems. WMSDE is working in collaboration with Dexter, a clinical data enablement platform designed to extract, normalise and prepare health data into analysis-ready datasets. This significantly reduces the time required for data analysis and improves the accessibility of health and care data available for research to improve patient care.

The opportunity

We are seeking clinicians from maternity and acute care backgrounds with an interest in health informatics and real-world evidence to dedicate one day per week (0.2 FTE) to support the evaluation of the Dexter tool within the WMSDE health data environment. This role offers a unique opportunity to use new datasets and advanced automated data extraction to undertake research that improve patient care, while evaluating and improving the underlying technology.

Key responsibilities

Clinical guidance: provide expert clinical input for the development and validation of clinical phenotypes within the Dexter platform.

Research collaboration: develop and deliver high-priority research projects using the using DEXTER on the above datasets, supported by technical and academic colleagues in BHP.

Engagement: act as a bridge between frontline clinical needs and technical data engineering teams to ensure research outputs are clinically relevant and actionable.

Training and communication: contribute to the development of a clinical and academic community engaged in approved use of data to improve patient care.

Who should apply?

We welcome interest from senior healthcare professionals in maternity and acute care backgrounds (including but not limited to: consultants, specialty registrars, senior midwives, pharmacists, AHPs, healthcare scientists, clinical academics) who:

  • Have a strong interest in either medical informatics, data-driven research or quality improvement.
  • Possess a working knowledge of, or wish to be trained on, the development of clinical phenotypes using structured data (e.g., SNOMED CT, ICD-10, OPCS DM&D), and observational research
  • Can secure the support of their department for a 1-day-per-week commitment.

Why join us?

The collaboration places you at the heart of one of the UK’s leading Secure Data Environments and health partnerships. You will work alongside a multidisciplinary team of data scientists and researchers, gaining invaluable experience in automated health data research.

How to apply

Interested candidates should submit a short statement of interest (max 500 words) and a CV outlining:

  • Your clinical background and area of expertise
  • Your experience or interest in health data science and proposal of the broad areas of interest you would want to focus on
  • Confirmation of departmental support for the time commitment

Deadline for submission: Thursday 6 August 2026.

Contact for enquiries and applications: Cassie Conway

Healthcare professionals invited to apply for new regional research programme

Following the launch of the West Midlands Regional Account for Clinical Researchers (WMRACR), we’re pleased to announce that the programme is now accepting applications from doctors, nurses, dentists, midwives, therapists and pharmacists.

WMRACR is a partnership led by the University of Birmingham and funded by the Medical Research Council (MRC), working with Aston, Keele and Warwick universities to increase the number of clinical academics across the region.

These awards are designed to support talented postdoctoral clinical professionals and other healthcare staff to develop competitive research careers. Support includes:

  • Protected research time for ~12 months, delivered within your current role; typically at 50% time.
  • Mentorship and tailored training
  • Opportunities for interdisciplinary collaboration
  • Access to a strong regional research network

Applicants must be based within a West Midlands NHS Trust or University.

Application details
Further details, including eligibility and application guidance, are available on the WMRACR website.

The deadline for the first cohort is Friday September 11th. 

The WMRACR programme team will be hosting a series of webinars to answer any queries you may have on this. To register for one of these please contact the University of Birmingham ICAT team on icat@contacts.bham.ac.uk 

  • Wednesday 8th July 12:00-12:30
  • Wednesday 15th July 14:00-14:30
  • Tuesday 21st July 09:30-10:00